
You see a few extra strands on the pillow. By lunchtime you’ve pictured a future in wigs. It’s a common spiral and most people never actually check whether it’s justified. They just grab a shampoo or a serum and hope for the best.

People use “hair fall” and “hair loss” like they mean the same thing. They don’t. Your scalp can go through two very different processes. One usually fixes itself. The other doesn’t, not without treatment. The two get confused so often that people end up wasting months, sometimes years, on the wrong fix.
Here’s how to actually tell them apart.
The Number Nobody Believes
Losing 50 to 100 hairs a day is normal. Not “acceptable.” Not “manageable.” Just normal. Your hair is built to do this. Your scalp holds around 100,000 follicles and they grow and rest on a staggered schedule, so losing a hundred strands barely dents the total.

That clump in the shower drain usually proves nothing, mostly because nobody actually counts. What matters is the pattern: real thinning building up over weeks or months, versus noticing a normal process for the first time.
Hair Fall: The Kind That Usually Fixes Itself
Doctors call this telogen effluvium, and once someone explains the term it brings real relief. The shedding spreads evenly across the scalp instead of concentrating in one spot, with no inflammation and no scarring. In some cases it affects up to half the scalp hair at once. That sounds alarming, but the follicles stay completely healthy underneath. They’ve simply entered their resting phase early.

What confuses people is the timing: the trigger usually happens two to three months before the shedding starts. A high fever, a stressful stretch, surgery, sudden weight loss, or a hormonal shift like childbirth can all flip the switch. Hair then falls out weeks or months after the event has already ended, which is exactly why almost nobody connects the dots on their own.
The Reassuring Part
New hair growing in underneath often pushes the old resting hair out, so the shedding that’s worrying you can actually be a sign that regrowth is already underway. Most cases settle within a few months once the trigger resolves. A smaller number turn chronic and linger longer, and those genuinely deserve a proper check instead of an indefinite wait.
Hair Loss: The Kind That Needs a Real Plan
“Just give it time” doesn’t work here. The most common form is androgenetic alopecia, also called pattern baldness, and it runs on a completely different mechanism. A hormone called DHT acts directly on the follicle, shrinking it a little more with every growth cycle until it stops producing visible hair.
The distinction that matters: hair fall is a cycle problem, temporary, and it usually reverses once you fix the trigger. Hair loss is a follicle problem. It progresses steadily, driven by hormones rather than circumstances, and rarely has one obvious trigger. It just builds quietly over months or years.
Pattern Is the Real Giveaway
Ordinary hair fall spreads evenly across the whole head. Hair loss shows up somewhere specific: a receding hairline, a widening part, thinning at the crown. And the two can happen together. Someone with early pattern hair loss can go through a stressful stretch and see a spike in shedding stacked on top of thinning that was already happening quietly. That overlap is exactly why untangling the two usually needs an actual scalp exam rather than a guess in the mirror. For the first few months they can look nearly identical.
The Category Most Articles Skip
Not everything fits into “temporary shedding” or “slow pattern thinning.” Sometimes you’ll see smooth, round, coin-shaped patches instead of general thinning. That points to something else: alopecia areata, an autoimmune condition where the immune system mistakenly attacks the hair follicles. It doesn’t behave like the other two types, so it responds best to early, specific treatment rather than a general approach.
How Specialists Actually Sort This Out
None of this needs to stay a guessing game. At Maynee Skin, Hair & Slimming Clinic, OMR, a proper evaluation starts with a simple conversation: when did it start, was there a specific trigger, does baldness run in the family, what does the pattern actually look like up close?
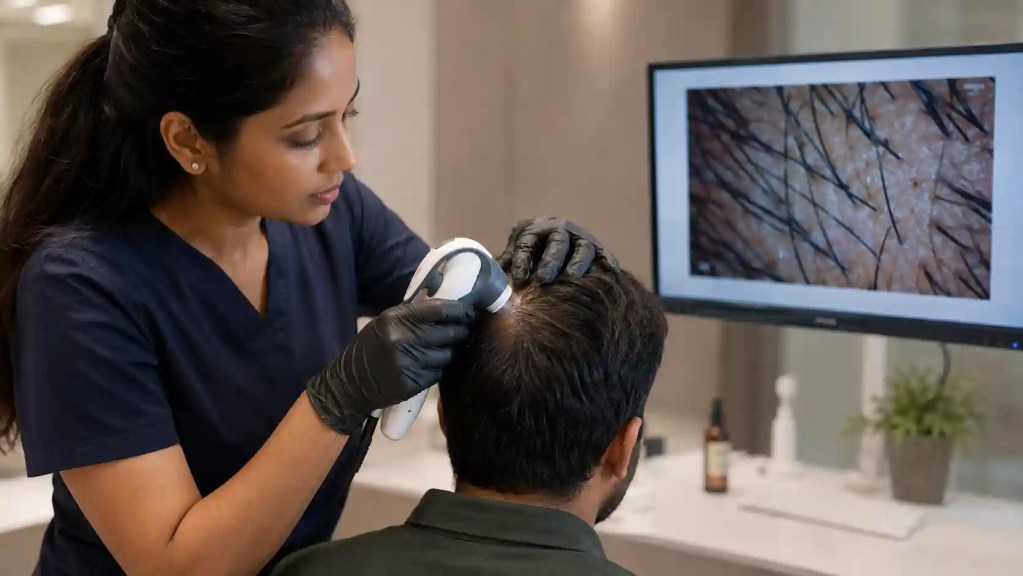
Trichoscopy often settles it. This quick, painless scan magnifies the scalp and shows what’s happening at the follicle level. Specialists sometimes run basic blood work too, checking thyroid function, iron, and vitamin D, since deficiencies in any of these can mimic hair loss symptoms even though they have nothing to do with genetics.
Why OMR Residents Ask This So Often
If you live around OMR or Sholinganallur, there’s a local pattern worth knowing. It comes up constantly in scalp consultations at Maynee’s OMR branch. Much of the groundwater there runs hard and mineral heavy, sometimes saline, and it strips the scalp’s protective barrier faster than softer water would elsewhere.

People notice a real jump in shedding after moving into the area and naturally assume the worst. Most feel relieved to learn it usually isn’t pattern loss at all. Water-related shedding behaves much more like ordinary hair fall. It aggravates an already sensitive scalp rather than attacking the follicle directly, and it tends to improve once the water exposure and scalp care get addressed properly. For a deeper look at this and other local factors, read the complete hair loss guide.
So, Which One Do You Actually Have?
Did it start suddenly, two or three months after a stressful event, illness, or big life change, spread evenly across the scalp? That points to ordinary hair fall, and time plus fixing the trigger is usually enough.
Has it built slowly over a year or more, following a specific pattern, with baldness running in the family? That points to hair loss, and it genuinely benefits from a real treatment plan at Maynee Skin, Hair & Slimming Clinic, OMR rather than patience.
Is it happening in distinct round patches instead of general thinning? That points toward something that needs its own specific approach.
Still not sure? That’s genuinely common, and you don’t need to keep guessing alone.
.
Frequently Asked Questions
Somewhere between 50 and 100 strands is considered normal, and given that your scalp holds roughly 100,000 follicles, that number barely makes a visible dent. What matters more than the count is whether you’re seeing genuine thinning build up over weeks or months, not just an ordinary day’s shedding you’re suddenly paying attention to.
Telogen effluvium is the medical term for temporary, excessive shedding, triggered by things like stress, illness, sudden weight loss, or childbirth, usually showing up two to three months after the trigger. It’s not the same as hair loss in the pattern-baldness sense. The follicles stay healthy, and most cases resolve on their own within a few months once the underlying cause is addressed.
Women’s hair fall often traces back to hormonal shifts, PCOS, thyroid changes, pregnancy, postpartum recovery, or menopause, on top of the usual stress and nutritional triggers. Hormonal causes are so common in women that the diagnostic approach often looks a little different than it does for men.
For men, genetic pattern baldness tends to be the leading long-term cause, though stress-related shedding, nutritional gaps, and scalp conditions like dandruff can all contribute on top of that, sometimes at the same time, which is part of why self-diagnosis gets confusing.
It’s real, not a myth. The same fungus responsible for flaking, Malassezia, can inflame the skin around the follicle and accelerate shedding in that area. Persistent dandruff alongside increased hair fall is worth addressing directly rather than only treating the hair loss on its own.
A receding hairline is a pattern, not random shedding. It reflects the follicle itself gradually miniaturizing in a specific area, which is the hallmark of androgenetic alopecia rather than ordinary telogen effluvium. This distinction is exactly why pattern matters more than volume when it comes to figuring out what’s going on.
Yes, genuinely. Significant physical or emotional stress can trigger telogen effluvium roughly two to three months later. It typically lasts a few months once the stressful period has passed, though a smaller number of chronic cases linger longer and are worth having properly evaluated rather than waiting out indefinitely.
Yes, meaningfully so. Smooth, round, coin-shaped patches point toward alopecia areata, an autoimmune condition, rather than ordinary diffuse shedding or hormonal pattern loss. It needs its own specific treatment approach. Worth getting checked rather than assuming it’s just “worse” regular hair fall.
It typically starts with a detailed history, timeline, and family background, followed by a close scalp examination. Trichoscopy, a simple magnified scan, often settles the question between conditions that look alike early on, and in some cases, basic blood work checking thyroid, iron, and vitamin D levels rules out deficiency-driven causes.
It’s a real, documented contributing factor, particularly in areas with high mineral content and coastal salinity, OMR being a notable example locally. That said, it tends to worsen an existing tendency toward shedding rather than being the sole cause on its own, which is why understanding the underlying diagnosis still matters more than switching to a shower filter alone.